
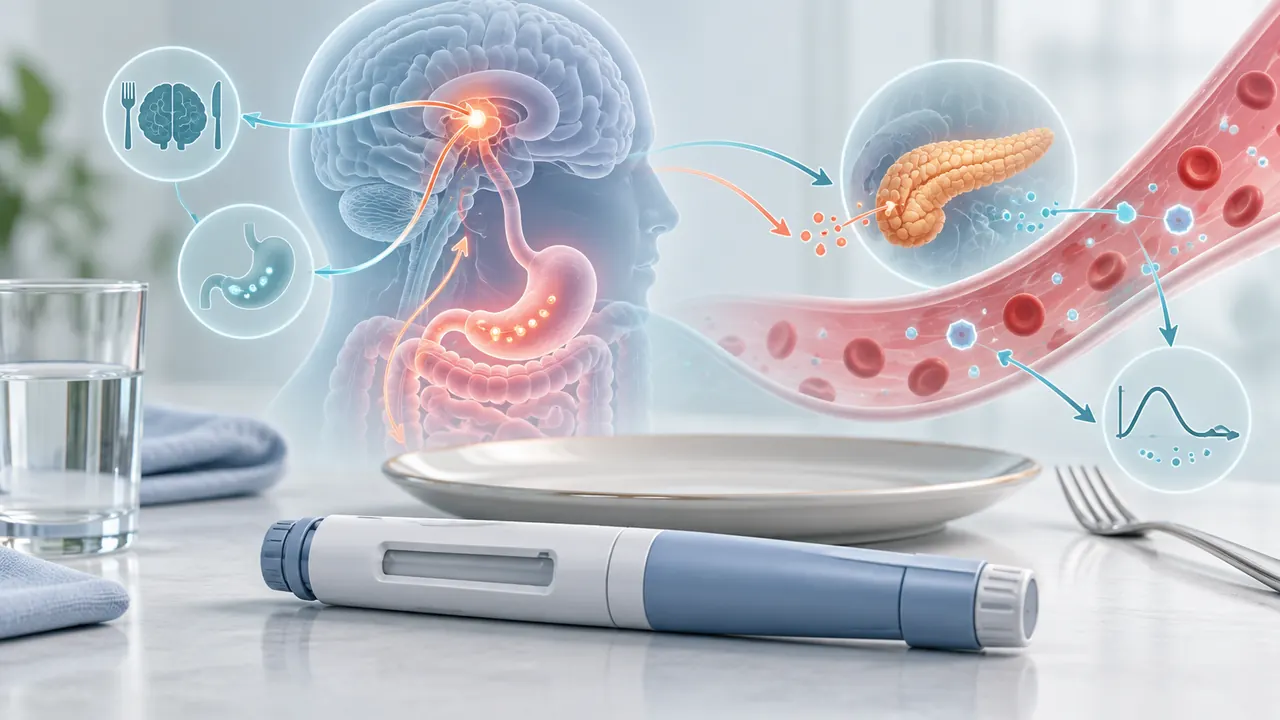
GLP-1 drugs did something unusual: they made a messy medical problem look simple.
For decades, weight loss advice circled around willpower. Eat less. Move more. Try harder. That advice was not completely wrong, but it was incomplete in a way that blamed patients for biology. Appetite, satiety, metabolism, environment, sleep, stress, genetics, and medications all push on body weight.
GLP-1 drugs changed the conversation because they act on some of that biology directly.
Quick answer
GLP-1 drugs are prescription medicines that mimic or amplify incretin hormone signals involved in appetite, fullness, insulin release, and stomach emptying. They can help some patients lose substantial weight and improve diabetes or cardiovascular risk factors, but they also require medical screening, dose management, side-effect monitoring, and a realistic plan for long-term treatment.
They are best understood as serious chronic-care medicines, not general wellness products.
What GLP-1 means
GLP-1 stands for glucagon-like peptide-1. It is a hormone involved in blood sugar regulation and appetite. Drugs in this family mimic or influence incretin hormones, helping the body release insulin when needed, slowing stomach emptying, and increasing the feeling of fullness.
Semaglutide is the active ingredient in Ozempic and Wegovy. Tirzepatide, used in Mounjaro and Zepbound, acts on GLP-1 and another hormone pathway called GIP.
The practical effect for many patients is a quieter appetite signal. Food can become less mentally loud.
Which drugs people usually mean
People often use "GLP-1" loosely, but the brand names are not interchangeable:
- Ozempic is semaglutide approved for type 2 diabetes.
- Wegovy is semaglutide approved for chronic weight management and, in specific adults, cardiovascular risk reduction.
- Mounjaro is tirzepatide approved for type 2 diabetes.
- Zepbound is tirzepatide approved for chronic weight management.
The distinction matters because dosing, insurance coverage, medical indication, and safety labeling differ by product.
Why the results got attention
Older weight-loss medications often produced modest results or had difficult safety histories. Newer GLP-1 and related drugs can produce far larger average weight loss, especially when combined with nutrition and lifestyle support.
That does not mean they work equally for everyone. Some people lose a lot of weight. Some lose less. Some cannot tolerate the side effects. Some stop because of cost or access.
The average result is impressive, but averages are not individual guarantees.
What the evidence actually supports
The strongest claims are not "these drugs make everyone thin." The better claim is narrower: in clinical use, semaglutide and tirzepatide can produce clinically meaningful weight loss for many adults with obesity or overweight with related conditions, and some GLP-1 medicines also have diabetes and cardiovascular indications.
The FDA-approved Wegovy label, for example, includes chronic weight management and reducing the risk of major adverse cardiovascular events in adults with established cardiovascular disease and obesity or overweight. The FDA-approved Zepbound label includes chronic weight management for adults with obesity or overweight plus at least one weight-related condition.
That does not make them interchangeable. It means the question should be "which medicine, for which patient, for which goal, with which risks?"
Why these drugs changed the culture
GLP-1 drugs did not just change medicine. They changed the social story around weight. For years, public conversation treated obesity mostly as a willpower problem. These drugs made it harder to deny that appetite regulation is biological.
That shift is useful, but it also creates new risks. A medicine can be legitimate and still be overmarketed. A treatment can help many patients and still be misused as a status symbol. The cultural swing from stigma to hype is not the same as understanding.
The better frame is medical realism: these drugs can be powerful tools for people with obesity, diabetes, cardiovascular risk, or related conditions, but they are not a universal wellness upgrade.
For adjacent health-evidence context, see creatine evidence, magnesium supplements, and vitamin D evidence. They are different subjects, but the same rule applies: ask what outcome was measured, in whom, and compared with what.
The side effects are not trivial
The most common side effects are gastrointestinal: nausea, vomiting, diarrhea, constipation, reflux, and reduced appetite. For some people these are mild and fade. For others they are disruptive.
There are also less common but serious concerns doctors watch for, including gallbladder problems, pancreatitis symptoms, dehydration, and interactions with other medical conditions. Muscle loss can become an issue when weight falls quickly without enough protein or resistance training.
These drugs should be treated like serious medicines, not cosmetic shortcuts.
What good treatment looks like
Good care is not just a prescription. It usually includes:
- screening for contraindications and relevant medical history
- a plan for dose escalation and side-effect management
- nutrition support, especially enough protein
- resistance training or activity guidance to preserve muscle
- monitoring for blood sugar, hydration, and gallbladder symptoms when relevant
- a realistic conversation about cost and duration
The muscle issue matters because losing weight is not the same as improving health. Rapid weight loss can include lean mass. Preserving strength, mobility, and metabolic health requires more than appetite suppression.
Access is part of the story
These medications are expensive, and insurance coverage varies widely. Supply shortages have also affected patients who use them for diabetes. That creates an uncomfortable distribution problem: the people who may benefit medically are not always the people who can access them.
There is also a follow-on market of compounded products, med-spa prescriptions, online clinics, and gray-area advertising. Some services are legitimate; others blur medical care with consumer marketing. The more popular the drugs become, the more important clinical oversight becomes.
The hardest part is stopping
Weight often returns after stopping treatment. That is not a moral failure. It reflects the fact that the medication was changing appetite and metabolic signals. When that effect is removed, the old signals can return.
This creates a difficult reality: for many patients, GLP-1 treatment may be long term. That raises questions about cost, insurance, supply, side effects, pregnancy planning, and what lifelong treatment means for a condition that society still moralizes.
The bottom line
GLP-1 drugs are not a miracle and not a scam. They are powerful medicines that reveal how biological weight regulation has always been.